DIAGNOSTIC MEDIAL BRANCH BLOCK
A cervical medial branch block numbs the two small nerves that supply a neck facet joint. Then it tracks what your pain does while the anesthetic works. If the pain goes, that joint was generating it. This is the only test that identifies facet-mediated neck pain. No imaging finding, blood test or physical exam sign does it, which is why the block exists.
What is a cervical medial branch block used for?
Facet joints (the small joints at the back of the spine) are a common source of lasting neck pain. Yet they are invisible as a pain generator on every scan. Degenerative change (the joints breaking down) at the facets is visible and nearly universal past middle age. It is also present in huge numbers of people with no pain at all. So the picture cannot tell you whether the joint you can see is the joint that hurts.
The block answers that directly. Numb the two medial branch nerves supplying a joint. Then ask what happened to the pain while the anesthetic was working. If it went, that joint was generating it. If nothing changed, it was not. You have just saved yourself a treatment aimed at the wrong structure.
Why one block is not enough
A single positive block has a false-positive rate high enough that treating on it produces avoidable failures. Placebo response, anesthetic spreading to nearby structures and simple expectation all contribute.
The answer is confirmatory blocks: repeating the block on a separate occasion before committing to ablation. That means more appointments. It is also the difference between a procedure that works in most selected patients and one with a reputation for disappointing. We spend an extra visit rather than treat a level nothing confirmed.
What you are asked to do, and why it matters
The diagnostic value lives entirely in your report afterward. You will be asked to rate the pain on a simple scale before the block. Then you rate it again at intervals over the next several hours.
Two instructions matter. Do the things that normally hurt. A block that abolishes pain you never provoked has told you nothing. And record it as it happens, rather than rebuilding it from memory that evening. The single most common reason a block cannot be read is a diary written from memory.
What happens during a cervical medial branch block?
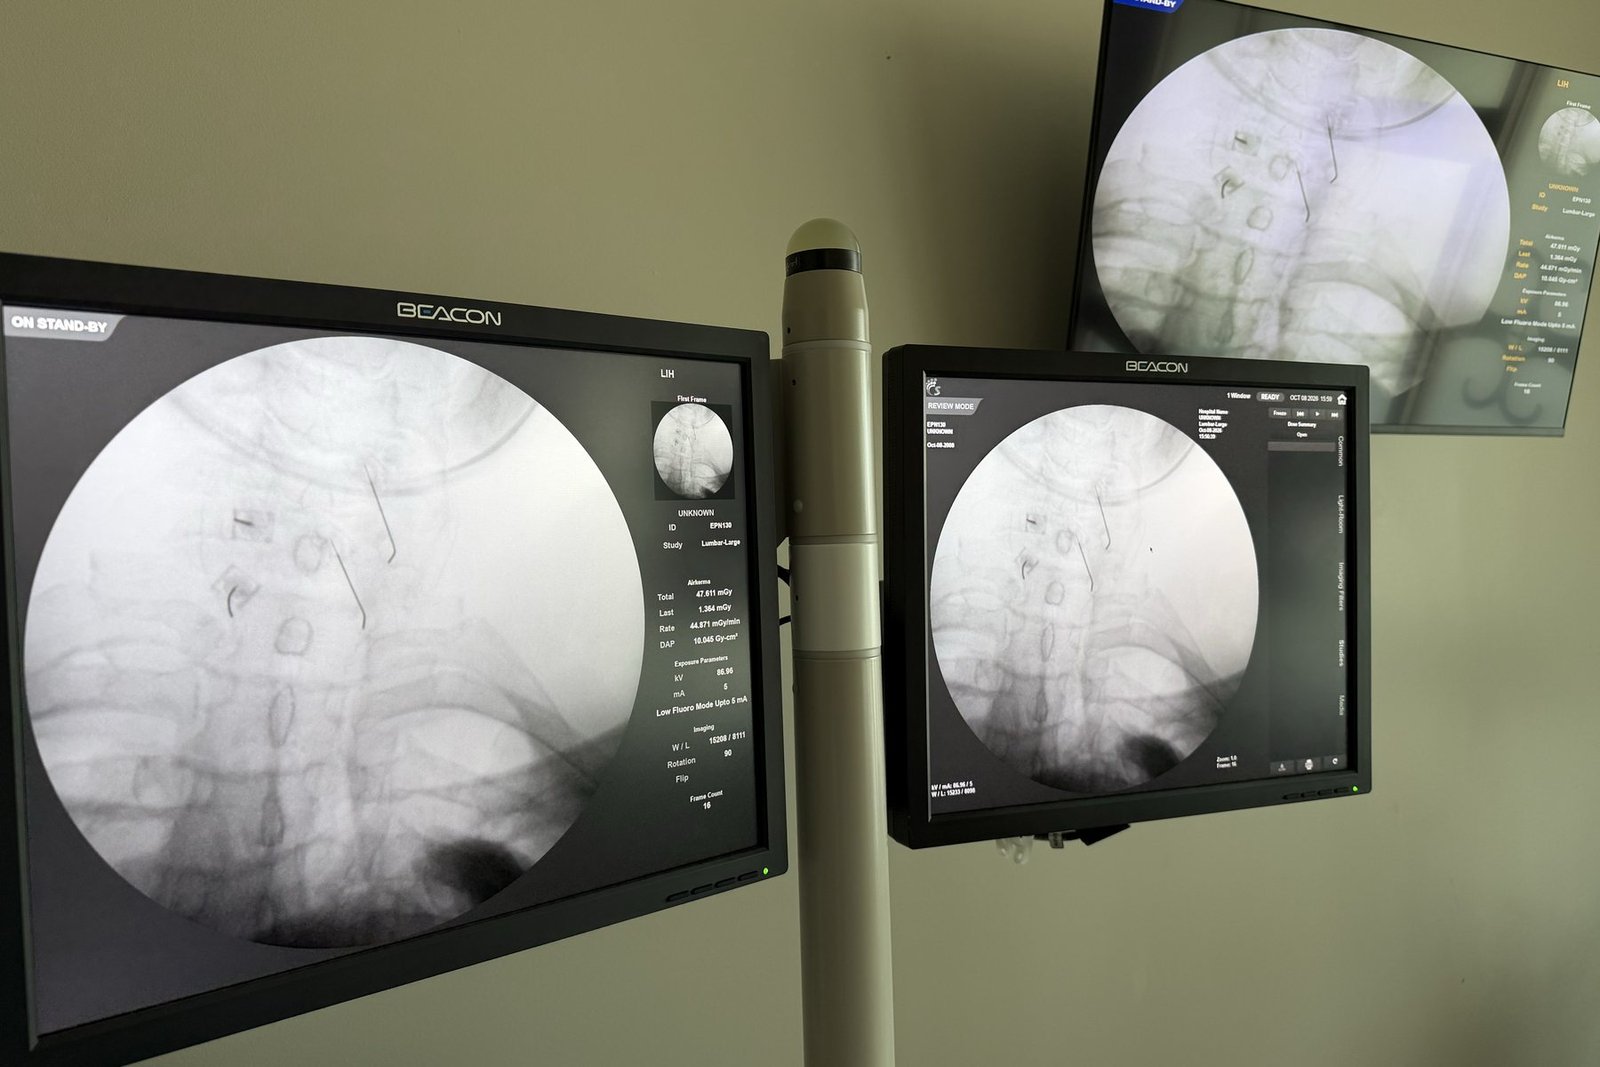
- You are seated or lying face down. The skin is numbed. Needles are placed under fluoroscopic guidance (live X-ray) onto the articular pillar (the bony column of the joint) at each target level.
- Contrast dye confirms the needle is where it appears to be. It also confirms the medicine is not going into a blood vessel.
- A very small volume of local anesthetic goes on each nerve. The volume is kept small on purpose. A generous volume spreads and gives a false positive.
- Fifteen minutes, no sedation, and you drive yourself home.
Sedation is avoided on purpose for a diagnostic block. A sedated patient cannot report reliably, and the report is the entire point of the procedure.
What do medial branch block results mean?
A clearly positive block identifies the target. That means the pain is substantially gone while the anesthetic works and returns as it wears off. A clearly negative block rules the joint out and redirects the workup. That is a useful result, not a wasted appointment.
An equivocal (unclear) block is the awkward one. The correct response is not to go ahead anyway. It usually means the pain has more than one source, or the wrong level was targeted, or the provocation was not enough. All three are worth knowing.
The diary is the test, so here is how to keep one
Write the number down before the injection. Then at thirty minutes, one hour, two, four and six. A simple zero-to-ten is fine and better than a description written from memory that evening.
Between those points, go and do the things that normally hurt. Turn your head to back up a car. Look up at a shelf. Sit at the desk that sets it off. A block that abolishes pain you never provoked has told nobody anything. It is the single most common reason a block comes back unreadable.
What the second block adds
The confirmatory block is done on a separate occasion. Sometimes it uses an anesthetic that lasts a different length of time. It is looking for consistency. Two concordant (matching) positives make the target about as certain as this specialty gets.
It is an extra appointment. It is also the difference between a radiofrequency procedure that works in most selected patients and one that gets a reputation for disappointing. We spend the visit rather than treat a level nothing confirmed.
Can you drive home after a medial branch block?
No fasting, no sedation, no driver required. Allow an hour. You will be asked to stay nearby for the first part of the observation window rather than going straight home. That is because the most useful period is the first two hours, and that time is better spent doing the activities that provoke pain than sitting in traffic.
What are the side effects of a cervical medial branch block?
Soreness at the needle sites for a day or two is common. Temporary unsteadiness or a heavy arm can occur if anesthetic spreads, and it resolves within hours. Serious complications are rare with imaging guidance, contrast confirmation and small volumes, and all three are used here. Vascular uptake (medicine entering a blood vessel) is the specific thing contrast looks for. It is the reason this is not done blind.
What people ask about diagnostic blocks
Does the block treat anything?
No, and it is not meant to. It is a diagnostic test using a short-acting anesthetic. Any relief lasting beyond a few hours is a bonus, not the purpose. What the facet joints actually do.
Why do I need two of them?
Because one has a meaningful false-positive rate, and the treatment that follows is not trivial. Confirming twice is what separates good outcomes from the published disappointments. Whiplash, and why the scan is normal. One positive result carries a false-positive rate that two do not.
What if the block does not help?
Then the facets are not your pain source, which is truly useful. It redirects the workup toward the nerve roots, the discs or a muscle driver. It does not leave you with an unexplained failure. How radiofrequency ablation works. A block that changes nothing has answered the question it was asked.
Is it dangerous?
It is a small-volume injection onto a bony target under imaging, and serious complications are rare. Soreness at the needle site for a day or two is common. Risks are covered at consent rather than glossed over. Ablation or fusion?
How long does it take to recover from a cervical medial branch block?
Recovery is short. The block takes about fifteen minutes, there is no sedation, and you drive yourself home. Soreness where the needles went in is common for a day or two. If the anesthetic spreads, an arm can feel heavy or you can feel a little unsteady, and that fades within hours.
Can pain get worse after a medial branch block?
The needle sites are often sore for a day or two, and that is expected. Your usual pain also comes back as the anesthetic wears off. That is part of the test. Pain that fades during the numbing window and returns afterward is exactly what points to the facet joint. Record it as it happens, not from memory that evening.
How long does the numbing from a medial branch block last?
The block uses a short-acting local anesthetic, so the useful window is a matter of hours. That is why the diary runs from before the injection through six hours. The first two hours are the most informative. Relief that lasts longer than a few hours is a bonus, not the purpose of the test.
Is a medial branch block worth it?
Yes, because both answers are useful. A clear positive, confirmed by a second block, identifies the facet joint to target with radiofrequency ablation. A clear negative rules the facets out. It redirects the workup toward the nerve roots, the discs or a muscle driver. Either way, you avoid a treatment aimed at the wrong structure. Each block takes about fifteen minutes.
Related reading
- Cervical facet syndrome
- Radiofrequency neurotomy
- Why your MRI is normal
- What happens at the first visit
- Cervicogenic headache
- Neck pain doctor in St. Louis
A block is a sided procedure — there is no way to anesthetize “the neck.” Why sidedness has to be established rather than assumed.
Get the level confirmed before anything is treated
The block is short, the answer is immediate, and a negative result is as useful as a positive one.
12174 Natural Bridge Rd, Suite 302
St. Louis, MO 63044
Next to DePaul Hospital, just off the 270 and 70 junction, west of the airport.
Sources
- Hurley RW et al. Consensus practice guidelines on interventions for cervical spine (facet) joint pain from a multispecialty international working group. Reg Anesth Pain Med, 2022. PubMed 34764220
- Manchukonda R et al. Facet joint pain in chronic spinal pain: an evaluation of prevalence and false-positive rate of diagnostic blocks. J Spinal Disord Tech, 2007. PubMed 17912133
- Manchikanti L et al. An Updated (2026) Best-Evidence Synthesis Appraisal of the Diagnostic Accuracy and Utility of Facet (Zygapophysial) Joint Injections in Chronic Spinal Pain. Pain Physician, 2026. PubMed 42370931
- Manchikanti L et al. Cervical zygapophysial (facet) joint pain: effectiveness of interventional management strategies. Postgrad Med, 2016. PubMed 26653406