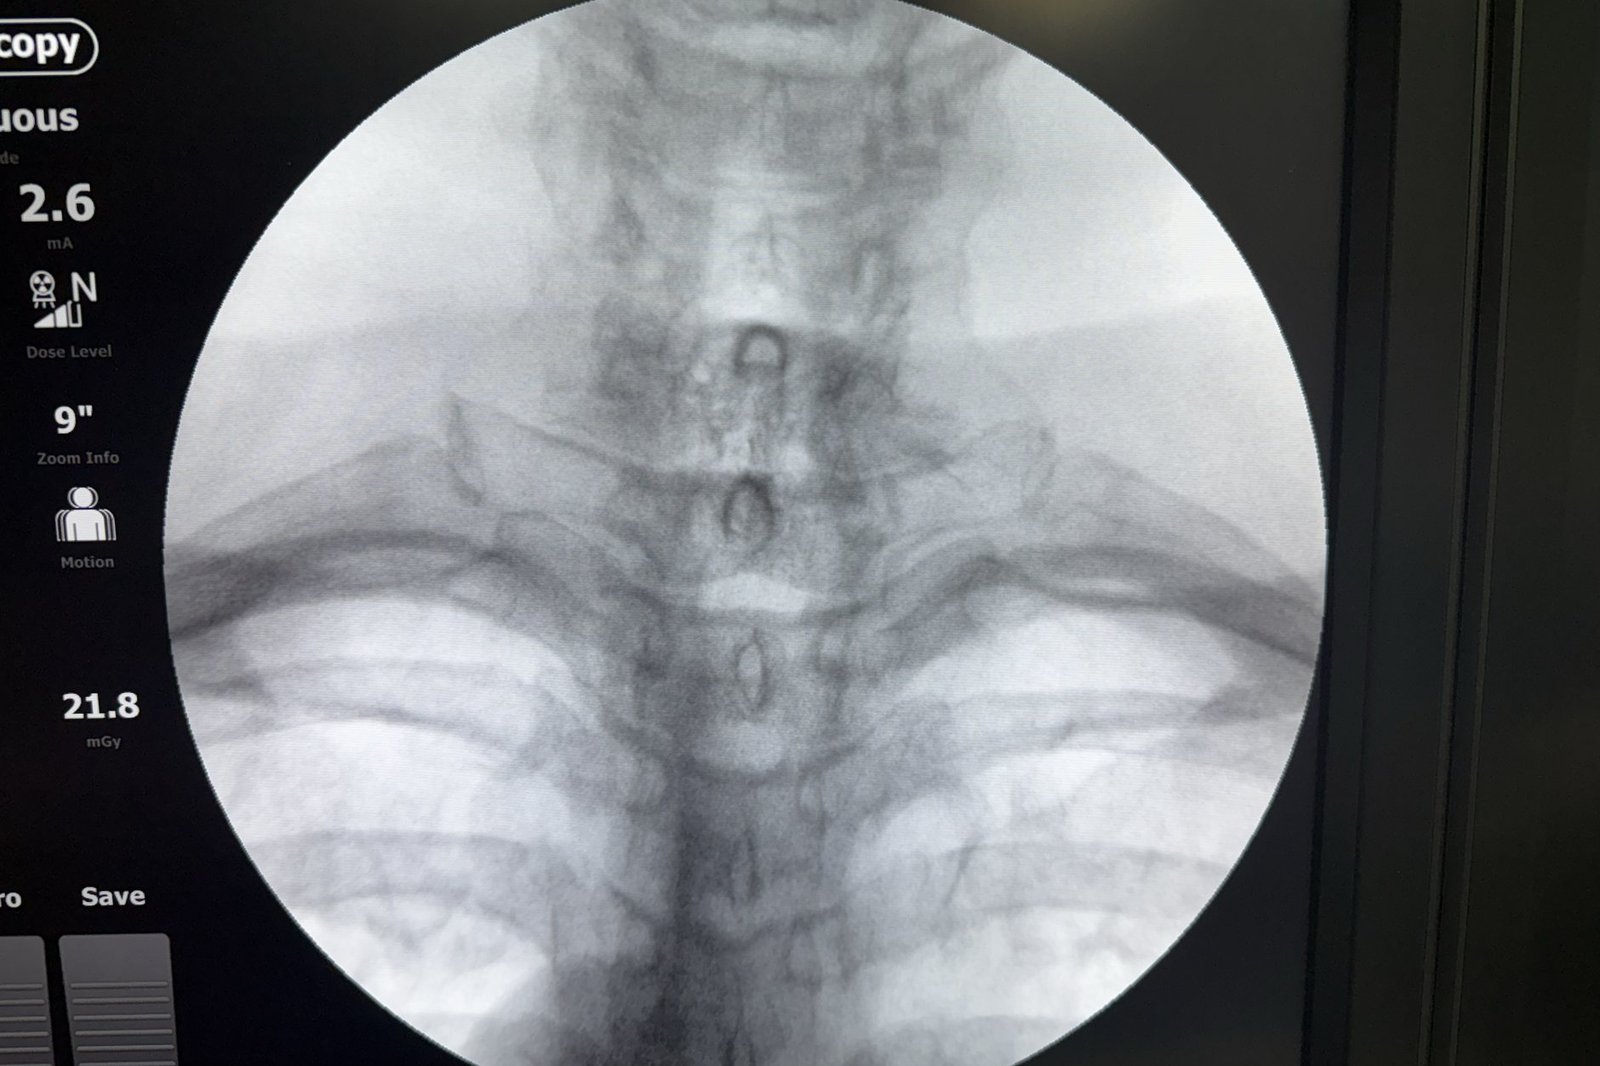
CERVICAL DISCOGRAPHY
Cervical discography injects contrast (dye) into a disc under fluoroscopy (live X-ray). You stay awake enough to report whether it brings on your pain. It is the only test that asks a disc whether it is the one that hurts. It is also the most argued-about.
What is a cervical discogram?
Contrast is injected into a disc under fluoroscopy while you stay awake enough to report what you feel. The question is not what the disc looks like — imaging already answers that. The question is whether putting pressure on this disc brings on your pain. And it is whether putting pressure on the discs next to it does not.
That concordant-pain response (it brings on the pain you know), with negative control levels, is the whole point. A disc can light up on contrast and still produce nothing familiar. That disc is not your pain generator, however degenerate it looks.
Why the argument exists, stated fairly
Three things drive it. Abnormal-looking discs are extremely common in people with no symptoms. So morphology (how a disc looks) alone proves nothing. Pain reporting during the procedure is subjective. It can be swayed by expectation and by psychological distress. And in the lumbar spine (low back) there has been a serious, well-publicized question. It asks whether the procedure itself speeds up degeneration in the injected disc.
Systematic reviews of cervical discography as a diagnostic test have reached measured rather than eager conclusions. The honest summary: it is a test with real diagnostic information and real limits. It is not a machine that hands out final answers.
What are the risks of a cervical discogram?
Discitis — infection of the disc — is the serious risk. It has been reviewed for cervical discography in particular. The rate is low, and it is not zero. A large analysis of cervical diagnostic disc injections laid out the complications in detail. That research is the reason the procedure is done with strict technique and antibiotic prophylaxis (antibiotics given ahead of time). It is also the reason it is not offered casually.
Esophageal puncture (a needle through the food pipe), vascular injury and hematoma (a pocket of blood) are the other named risks of the cervical approach in particular. None of that means the test should never be done. It means the test should be done when the answer will change a decision.
When is a cervical discogram needed?
- Considered when a specific surgical decision hinges on which level is symptomatic (causing the symptoms), and every less invasive test has left that unclear.
- Considered where imaging shows multilevel degenerative change and the clinical picture cannot pin down one level.
- Not used as a screening test, a routine part of a workup, or a way of confirming what the MRI already suggested.
- Not used where facet-mediated pain (pain from the facet joints) has not been ruled out first. A medial branch block is far less invasive. It answers a question that is commonly the right one, and it answers it first.
What we do first, essentially always
The facet joints, because cervical facet pain is common. It is testable with a low-risk block and treatable with radiofrequency ablation. The nerve roots, where the picture is radicular (pain running down the arm). The muscles and the upper cervical segments, where headache leads the picture. Discography sits at the end of a sequence, not near the front of one.
We also do not run this test on somebody who is not a surgical candidate and does not want to become one. That is because the result changes nothing for them.
If you have been offered it elsewhere
Reasonable questions to ask: What decision will this test change? What happens if the result is equivocal (unclear)? What is your discitis rate? Has facet-mediated pain been excluded first? A clinician doing this well will have clear answers to all four.
What happens during a cervical discogram?
You arrive fasted. An intravenous line goes in for antibiotic prophylaxis. The procedure itself takes under an hour for a two- or three-level study. No sedation is used; you stay awake under local anesthetic. You stay for observation afterward. Most patients drive themselves home. If an arm or leg feels weak or numb, have someone else drive until that wears off.
The information is collected in real time, level by level. It is written down as it happens, not rebuilt afterward. A post-procedure CT is often obtained. That is because it adds morphological information (detail about the disc’s shape) that the injection alone does not give.
The instruction we give beforehand
Report what you feel, including nothing. The value of the test rests entirely on the negative levels — a study where every disc hurts carries no information at all. It is usually a sign that central sensitization (an overamped nervous system), rather than a single disc, is driving the picture.
That is not a failed test. It is a truly useful answer. It points the treatment plan somewhere completely different.
What a positive result actually buys you
It narrows a surgical decision from a range of plausible levels to one. And it does so using your own pain report, not a conclusion drawn from imaging. In a person heading toward a fusion, that is not a small thing — operating on the wrong level is one of the recognized routes to failed neck surgery. Once a fusion is in place, it is not reversible.
What it does not buy you is a guarantee. Say you get a concordant response at one level and clean controls. Even then, results after surgery for discogenic (disc-driven) neck pain vary more than results after surgery for a compressed nerve root. Anybody presenting this test as a predictor of a good result is overselling it. We say so before the needle, not after the operation.
The alternative we reach for far more often
Cervical facet joints account for a large share of chronic axial neck pain (long-lasting pain in the neck itself), particularly after whiplash. They are testable with a low-risk block. They are treatable with radiofrequency ablation that lasts months and can be repeated. The risk profile is not comparable — there is no disc entered and no infection risk of the same order. There is also no question about speeding up degeneration.
That is why the sequence on this site puts medial branch blocks first for axial pain. It keeps discography for the narrow group where the answer will change a decision. That decision is already close to being made.
What people ask about discography
Is it painful?
Reproducing your pain is the purpose, so yes — briefly, at the level that is symptomatic. That is the information. Local anesthetic numbs the skin and the needle track, not the disc itself. What a herniated disc does and does not explain. It is the one procedure designed to provoke, and the others feel nothing like it.
Am I awake for it?
Yes, on purpose. Sedation deep enough to remove the pain report removes the test. No sedation is used; you stay awake under local anesthetic. What a compressed root actually causes. Being awake is what makes the answer usable.
Could it damage the disc?
This has been studied seriously, mainly in the lumbar spine. It is one of the real reasons the procedure is used sparingly rather than routinely. We treat it as a real concern, not a theoretical one. What a normal scan does and does not rule out.
Why do you do the facet blocks first?
Lower risk, and a higher pre-test probability in most neck pain. And a treatment that follows directly from a positive result. Order matters. Cervical disc herniation.
Is a discogram considered surgery?
No. It is a diagnostic test done through a needle under live X-ray guidance. It is not an operation, and it treats nothing. Contrast goes into each disc being studied while you stay awake enough to report what you feel. Its only job is to show which level brings on your pain, and which levels do not. That happens before a surgical decision is made.
How long does a cervical discogram take?
The procedure itself takes under an hour for a two- or three-level study. You arrive fasted, an IV line goes in for antibiotic prophylaxis, and you stay for observation afterward. A CT scan is often done right after the injections. That is because it adds detail the injection alone does not give. Most patients drive themselves home. Normal activity, including work, resumes within two to four hours. If an arm or leg feels weak or numb, have someone else drive until that wears off.
What happens after a positive discogram?
A concordant response at one level, with neighboring discs that stay quiet, narrows a surgical decision. It goes from several possible levels to one. It is not a guarantee: surgery for disc-driven neck pain has more variable results than surgery for a compressed nerve root. If every disc hurts, that points to central sensitization rather than one disc. Then the plan moves in a different direction.
Related reading
- Cervical medial branch block
- Cervical facet syndrome
- Cervical radiofrequency ablation
- Cervical radiculopathy
- Why your MRI does not explain it
- Failed neck fusion
It is the one test designed to provoke your pain, which is worth knowing beforehand. What the others feel like by comparison.
Ask what the test would change before agreeing to it
We are happy to review whether discography is the right next step, or whether a lower-risk test answers the same question.
12174 Natural Bridge Rd, Suite 302
St. Louis, MO 63044
Next to DePaul Hospital, just off the 270 and 70 junction, west of the airport.
Sources
- Manchikanti et al. Systematic review of cervical discography as a diagnostic test for chronic spinal pain. Pain Physician, 2009. PubMed 19305482
- Kapoor et al. Systematic review of the incidence of discitis after cervical discography. Spine J, 2010. PubMed 20171935
- Zeidman et al. Complications of cervical discography: analysis of 4400 diagnostic disc injections. Neurosurgery, 1995. PubMed 7501104
- Pinto et al. Provocative Discography: Diagnostic Efficacy and Safety in Symptomatic Degenerative Disk Disease. Clin Spine Surg, 2022. PubMed 35894509
- Gokaslan ZL et al. Utility of provocative discography. World Neurosurg, 2014. PubMed 24534063